

Arch development is a collective term that describes the purpose of a variety of appliances. Used to gain both arch width and arch length, these appliances range from the simple Schwarz appliance (with lap spring) to the high-speed, rapid palatal expanders. They may utilize orthodontic movement, orthopedic movement or a combination of both — and may be either fixed or removable. With proper design, expansion appliances may be used to move teeth on either side of the arch unilaterally or bilaterally. They may be used to relieve crowding in the posterior segments, develop underdeveloped pre-maxillas, reposition retroclined anteriors, and relieve anterior crowding.
There are many indications for arch development. In children, the overwhelming majority of lateral expansion appliances are used to treat crossbites, crowded anteriors with an excessive overjet, or a combination of these conditions. In adults, arch development appliances are mainly used to correct crowding in the anterior region, upright lingually tipped posterior segments back over the basal bone, distalize mesially inclined molars, correct retroclined anteriors, and, in conjunction with straight wire therapy, round out narrow arches and align the occlusal planes. Arch development is also important for patients who need therapy to correct a skeletal problem.
To help you choose the correct appliance, we have broken down the vast array of appliances into several distinct groups based upon their usage and type. The categories are:
- Lateral Development with Removable Appliances
- Lateral Development with Fixed Appliances
- Anterior/Posterior Development with Removable Appliances
- Anterior/Posterior Development with Fixed Appliances
- Combination Removable Appliances for AP/Lateral Development
- Combination Fixed Appliances for AP/Lateral Development
- Differential Development with Removable Appliances
- Differential Development with Fixed Appliances
Featured Appliances

Upper Schwarz Appliances
A narrow maxilla is one of the most common orthodontic problems seen in a developing child. Left untreated, it can lead to severe crowding and cause the occurrence of an anterior or posterior crossbite.
It can also inhibit the normal development of the mandible, creating a skeletal Class II. The Schwarz appliance is the most frequently used removable appliance to develop a narrow arch. This appliance works by turning the expansion screw in the center of the palate one-quarter turn once or twice a week.
This slow expansion allows the acrylic to place pressure on both the palatal tissue and the teeth in a lateral direction. As the arch develops the palate will drop, so adjustment of the acrylic in the palatal region will be necessary throughout treatment. Although removable appliances tend to tip teeth as they are moved buccally, expansion is slow enough that normal occlusal function is usually sufficient to maintain their normal inclination. In this example, individual recurved springs are used to move #7 and #10 into position as space is created. Note – These appliances can be made in different colors, designs and with decals. (Please see color chart in the “Reference Section”) This is a great way to motivate your patients.

Three Screw Sagittal
It is not unusual to see cuspids blocked out of the arch form.
In order to properly select an appliance to treat this problem, it is imperative that the practitioner understand the underlying cause of malocclusion. In this example, arch length is deficient because the patient lost her primary molars early. The first molars and bicuspids erupted mesially, and the arch is also slightly underdeveloped laterally due to a finger habit. To make room for the cuspids, both arch length and width need to be regained. Specifically, arch length needs to be gained by distalizing the posterior segments using this Three Screw Sagittal and its third (midline) expansion screw. As a general rule, the midline screw is activated first. Engaging it will provide the additional arch width desired and create enough lateral force to set up the anchorage needed to move the posterior segments distally. Keep in mind that second molars are not present. Once second molars have erupted, distalization of the posterior segments becomes very difficult with this design. Note: Many practitioners prefer adding cuspid retraction springs to this design so they can guide the cuspids into position as the space for them is made available.

Quad Helix U
The Quad Helix provides continuous, controlled force for a variety of applications.
It may be used for rotation or stabilization of molars, expansion or contraction of the arch, and even to assist in thumb, finger or tongue habit control. The principle advantage of the Quad Helix is that it allows for a differential amount of expansion in the anterior and posterior region of the arch. The appliance can either be soldered to the bands or attached via vertical or horizontal brackets. When it is soldered (as shown), all desired expansion must be adjusted into the appliance prior to cementation. If you choose the fixed/removable approach, adjustments can be made throughout treatment. Hint: Should you choose to use the soldered design, always request that the working model be returned with the appliance. The appliance can then be activated out of the mouth, seated back on the model, and tied with dental floss — across the arch from lingual arm to lingual arm — into a passive position. Once the appliance is fully seated and the cement has set, the dental floss can be cut and removed.
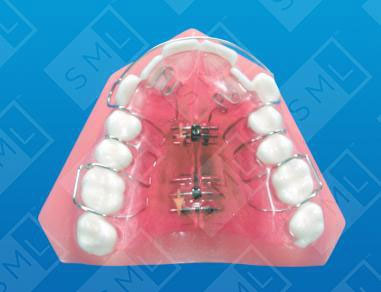
Upper Adult Expansion
Although arch development is more commonly used in the treatment of developing children, arch expansion appliances can be successfully used to treat adults.
They are particularly effective when the posterior teeth are lingually tipped in conjunction with the arch being narrow. A typical custom appliance, consisting of lingually tipped posteriors and crowded anteriors, is shown here. When using this appliance with an adult dentition, lateral development can be greatly enhanced by the addition of a second expansion screw. This ensures uniform anterior-posterior pressure and affords more stability as the screws reach the limits of their threads. Note: A small amount of differential expansion can be accomplished by adjusting these screws at a different rate. Care must be taken, however, to avoid cracking the appliance.

Reduced Acrylic Schwarz
Some patients simply cannot tolerate the acrylic extensions found in the standard Schwarz Appliance.
The Reduced Acrylic Scwarz is ideal for patients who have a severe gag reflex or experience serious difficulty speaking while wearing a full coverage maxillary appliance. The horseshoe shape of the palatal acrylic allows more space for the tongue, while still providing necessary anchorage for lateral arch development.

Schwarz with Posterior Bite Plane U
Bilateral posterior crossbites are typically the result of an underdeveloped maxilla.
Reasons for this occurance may include abnormal tongue posture, irregular swallowing pattern, obstructed airway caused by allergies. When a patient presents a bilateral crossbite, a Schwarz Appliance with Posterior Occlusal Coverage can be used. Occlusal coverage opens the vertical and is typically finished flat to allow for the quick resolution of the crossbite — without affecting the opposing dentition. By wrapping the occlusal acrylic over the buccal cusp tips, tipping of the dentition is kept to a minimum. Turning the expansion screw one-quarter turn a week exerts a slow, constant pressure on the teeth and bone. This arch development moves the posterior segments buccally out of crossbite and, in the process, drops a high-vaulted palate opening the nasal airway. Once the crossbite is corrected, the occlusal coverage should be removed — this allowing the patient to function into a normal occlusion. Note: As the high vault drops with expansion of the arch, adjustment of the acrylic on the palatal side of the appliance may be necessary to ensure proper seating of the appliance.
IMPORTANT: Recognition and treatment of a posterior crossbite early in a child’s development is essential. When left untreated, it can lead to numerous serious medical complications, e.g. Class II skeletal deformity, TMJ dysfunction, and airway obstruction.

Lower Schwarz with Midline Correcting Spring
When a primary cuspid is lost prematurely during the mixed dentition stage, the anteriors can shift off of the midline.
This creates a loss in arch length in that quadrant and blocks the eruption of the adult cuspid. It is not uncommon to see this type of arch length loss associated with a deficiency in arch width…and it is possible to correct both problems with one appliance. To correct a narrow arch and a midline shift with a removable appliance, simply add a midline correction spring to a standard Schwarz appliance. As shown, the midline correcting lap spring attaches to the right side of the appliance, runs along the lingual of the anteriors and finally wraps around the distal of the left lateral incisor. As the appliance is expanded laterally, this spring will pull the anteriors back to the midline. Once the midlines are aligned, the end of the spring that wraps around the lateral should be straightened out or cut off.

Lower Bowbeer L
The Lower Bowbeer appliance is a popular modification of the Schwarz design.
It is most commonly used when treating adults who have both a narrow arch and lingually tipped posteriors. Since it is designed without clasps, it is often used in conjunction with full arch bracketing in order to expedite treatment. The design is extremely esthetic and its small size makes it less likely to affect the patient’s speech. For all of these reasons this appliance is often preferred over other designs.

Williams Expander
An underdeveloped maxilla, abnormal tongue posture and aberrant swallowing patterns are some of the causative factors leading to a crowded narrow mandible.
In conjunction with maxillary appliance therapy that directly addresses these factors, appliances are available that will develop the constricted mandible and unravel the lower anterior crowding. The Williams Expander is a fixed appliance that is used during the early mixed dentition stage. It is designed to develop the lower arch and create normal spacing for the alignment of the permanent lower incisors and cuspids.
The framework of the appliance consists of a specially designed midline expansion screw soldered to two long sections of hollow tubing that run along the lingual aspect of the posterior segments. This tubing accepts a preformed .016 or .018 NiTi arch wire that rests against the lingual of the incisors. As the expansion screw is activated and the appliance widens, the NiTi wire expresses itself labially and aids in un-crowding the incisors.
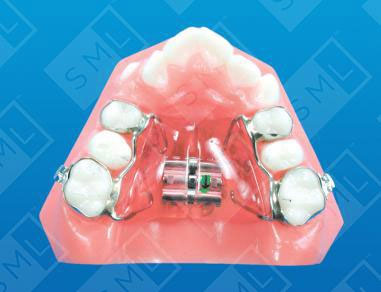
Haas “Memory” Transverse Expansion Appliance
The Haas “Memory” Transverse Expansion Appliance utilizes acrylic to support a spring-loaded expansion screw.
Adjusting the spring-loaded expansion screw — three 90-degree turns once every three days — delivers a continuous positive biologic force of about 500g over a distance of 0.8 to 1mm. Many practitioners prefer this appliance over the coil-spring activated RPE appliances. Because acrylic closely contacts the palatal mucosa, more bodily movement and less tipping occurs. The forces generated by the appliance are applied to the teeth and the palatal tissues. Caution: If hygiene is not carefully monitored, acrylic can cause serious inflammation. Note:Pre-formed bands may be selected and sent with the prescription or bands may be custom fit. Because this appliance uses four bands for retention, seating of the appliance can prove challenging.
Recommended:
- Leave separators in place until the delivery appointment.
- When the path of insertion is a problem, apply gentle pressure to allow seating over time.
- Cement bands with a glass ionomer cement.
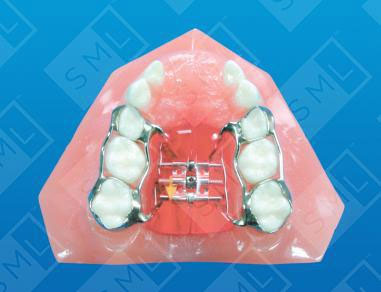
Haas Suture-Expanding Appliance
In patients with severe maxillary constriction in early permanent dentition or those who have moderate maxillary constriction in late adolescence, the Haas is the suture-expanding appliance of choice.
Acrylic supports the screw and adds extra stability. The acrylic closely contacts the palatal mucosa because Haas believed that more bodily movement and less tipping occurred with the presence of the palatal coverage. Forces are generated not only against the teeth, but also against the soft and hard palatal tissues. Caution: I hygiene is not carefully monitored, acrylic can cause serious inflammation. Note: Pre-formed bands may be selected and sent with the prescription or bands may be custom fit. Because this appliance uses four bands for retention, seating may present challenges.
Recommended:
- Leave separators in place until the delivery appointment.
- When the path of insertion is a problem, gentle pressure will often allow it to seat over time.
- Cement bands with a glass ionomer cement.

Rapid Palate Expansion (R.P.E.) 4- Banded Hyrax
The Rapid Palate Expansion 4-Banded Hyrax Appliance can be used successfully in patients with mild-to-moderate transverse constriction when they are in the late mixed or early permanent dentition (sutures presumably still patent).
This appliance eliminates the palatal acrylic, using an all-stainless metal framework instead…and although this design makes it much easier for the patient to keep clean, there is a greater chance that fewer skeletal — and more dentoalveolar — adaptions will be observed. Note: Pre-formed bands may be selected and sent with the prescription or bands may be custom fit. In addition, because this appliance uses four bands for retention, seating can present challenges.
Recommended:
- Leave separators in place until the delivery appointment.
- When the path of insertion is a problem, gentle pressure will often allow seating over time.
- Cement bands with a glass ionomer cement.

Direct Bond Suture Expansion
The Direct Bond Suture Expansion uses direct bond occlusal pads for retention, instead of banding 1st bicuspids and 6-year molars.
This key feature not only facilitates movement when a crossbite is present, but, because it covers the buccal cusp tips, also prevents tipping. Add in the rigid framework and you have a design that creates a movement primarily orthopedic in nature — especially beneficial for patients in the early mixed dentition stage or early adult dentition stage. Not recommended for patients who are in the late stage of mixed dentition — loose or exfoliating teeth will greatly compromise appliance anchorage. Note: When delivering this appliance, be sure to maintain a dry environment. Special instructions (along with all necessary supplies) can be provided via SML.

Bonded R.P.E. w/Lap Spring and Rests
During the early stages of adult dentition, second molars are often still erupting.
When placing a Bonded R.P.E. during this time, you will typically want to leave the partially erupted second molars free of the occlusal acrylic. To control their vertical development, simply prescribe occlusal rests. These rests can be adjusted or removed at any time. Adding anterior lap springs resolves anterior crowding — especially important when the anteriors are in an end-to-end or mild crossbite. The springs can be adjusted intraorally (with three-prong pliers). (Hint: Only apply bonding agent to the buccal and lingual surfaces. Do not apply the bonding agent to the occlusal surface. This makes the appliance difficult to remove.)

Multi-Action Hyrax
The CD Multi-Action Hyrax constitutes another solution for accomplishing distal bodily movement of the first molars while expanding the arch laterally.
It incorporates the use of NiTi coil spring, compacted onto buccal and lingual bars that run from the bicuspids to the molars. The bars are soldered to the bicuspid bands and run through tubes which are soldered to the molar bands. As the coil expresses itself, the molars slide distally along the bars in a bodily fashion. Note: Once molar position is established (and the arch is expanded), a holding arch is usually placed. The bicuspids and cuspids are brought back in the arch form — one at a time — using fixed mechanics.

Swing Lock Expander
Many patients exhibit a V-shaped or Gothic arch form as a result of an abnormal habit or an airway problem experienced during development.
When this occurs, the arch may only be narrow in the anterior region. Therefore, use of an expansion appliance that expands equally in the posterior and anterior region would be contra-indicated. To overcome said problem, the Swing-Lock Expander has been designed with an expansion screw and a posterior hinge. It gains anterior space without disturbing the posterior bite relationship, and since the expansion screw and the hinge are separate pieces, it is possible to keep the palatal acrylic thickness at a minimum and thus ensure greater patient comfort. Be advised that this design is only effective for an expansion of up to 4mm. If additional expansion is required, fabricate a second appliance or utilize an appliance with a larger fan screw. Note: As in all removable expansion appliances, activation of any of the springs should take place after space has been created via the expansion process.
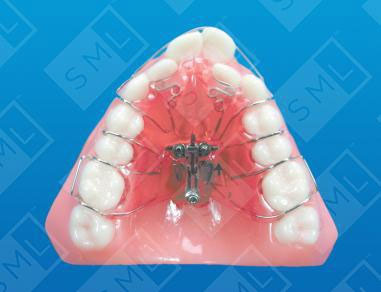
Wipla Swivel Plate
When the maxilla is significantly more narrow in the anterior region than in the molar region (and crowding is severe), a “Wipla” can make it possible to expand the arch and correct crowding without disturbing the posterior bite relationship.
The expansion screw is hinged in the posterior segment, confining expansion to the anterior region. The anterior portion of the screw pivots, allowing up to 8mm of expansion. Note: Since this screw is available in only one size, it may not fit all cases. When such is the case, the Swing Lock Expander is a viable alternative.
Upper Jackson
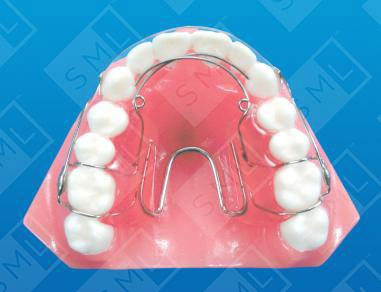
The Upper Jackson Appliance was one of the original removable expansion appliances.
Because it requires careful adjustment of the body wire, it’s popularity has waned since the advent of the simple-to-adjust expansion screw. Still, when a differential amount of development is needed throughout the arch, the Upper Jackson is still an excellent appliance for the job. It can be adjusted at the body wire with 139 Bird Beak Pliers or at the acrylic extension with three-prong pliers. Lap springs control the anteriors, while the open palate promotes proper tongue position, thus helping to maintain lateral development.
Lower Jackson
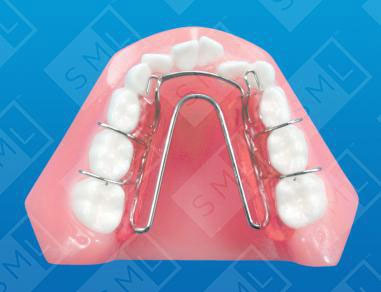
The Lower Jackson active expansion appliance is well suited for the mixed dentition stage of growth where lateral development of the lower arch is indicated.
The “pumping” action makes it particularly effective and produces rapid results. Since the upper arch develops faster than the lower, it is not uncommon for a doctor to prescribe an Upper Schwarz and a Lower Jackson to keep pace with the upper. Typical activation involves adding a uniform 3mm to 4mm lateral adjustment to the body wire — but the unique design of this appliance makes it possible to differentially expand the arch in both the anterior and posterior regions. Note: Some patients find this appliance uncomfortable if care is not taken to relieve the acrylic from the lingual-inferior undercut.

Basic Maxillary Crozat
The Basic Maxillary Crozat typically clasps the first permanent molars and is used primarily for lateral development.
Once this is accomplished, auxiliary attachments, e.g. lap springs, labial bows, pins, putters, appropriate inter-maxillary elastic hooks, can be added to the basic appliance to continue treatment as required.

Basic Mandibular Crozat w/ Lingual Springs
The Basic Mandibular Crozat w/Lingual Springs is used simultaneously with the Maxillary Crozat for lateral arch development.
As with the maxillary appliance, auxiliaries can be attached to the basic appliance (as required). Appliance shown includes the added lingual lap springs — to align the incisors and the distal extensions, thus helping to develop the second molars.
Interceptive Crozat U/L
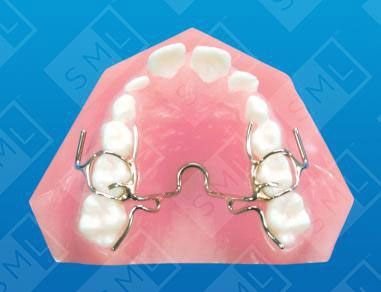
Crozats can be used for treating the young patient in mixed dentition.
Shown here, the Crozat Clasps are attached to the primary second molars, with extensions to the erupting six-year molars.The extensions are used to develop the arches by moving the permanent molars buccally. Note: In order to effectively employ these appliances in this situation, the primary second molars must have substantial root structure.
Phase I Crozats U/L
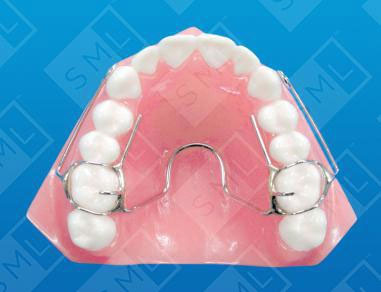
Phase I Crozats are used primarily for the arch development phase of a comprehensive treatment plan — a plan that includes straight wire fixed appliances for the final alignment of individual teeth.
Shown here, the upper appliance has Class II hooks added, while the auxiliary springs on the lower appliance are soldered to the body wire (rather than the mesial extension). Some prefer this for ease of adjustment. Note: The lower lap springs only effect the incisors while individual push springs are placed on the cuspids. This ensures more individual tooth movement.
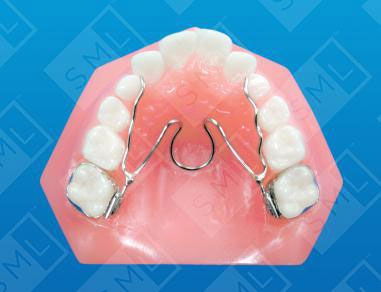
Porter Appliance
The Fixed Porter Appliance is designed to allow for a differential amount of expansion in the molar and cuspid/bicuspid region of a constricted maxillary arch.
Lateral pressure is placed on the banded molars by adjusting the loop with the flat side of #139 pliers. The primary molars, bicuspids and cuspids can be adjusted independently by adjusting the lingual arms. Since it is typically easier to adjust an appliance out of the mouth, sliding vertical or horizontal brackets (as shown) can be fitted on the lingual aspect of the molar bands — to facilitate removal of the wire without disturbing the banded teeth.

Bonded R.P.E. w/Lap Springs
The best time to use a Bonded R.P.E. with Lap Springs is with a mixed dentition patient.
Besides correcting a crossbite, it has been shown that expansion of the maxilla during the early mixed dentition stage may lead to a spontaneous correction of other occlusal disharmonies. For example, expansion of the upper arch in a skeletal Class II can allow the mandible to come forward on its own. Adding anterior lap springs resolves anterior crowding — especially important when the anteriors are in an end-to-end or mild crossbite. Springs can be adjusted intraorally (using three-prong pliers). Note: A Bonded R.P.E. is not recommended for patients who are in the late stage of mixed dentition. Loose or exfoliating teeth will greatly compromise appliance anchorage.
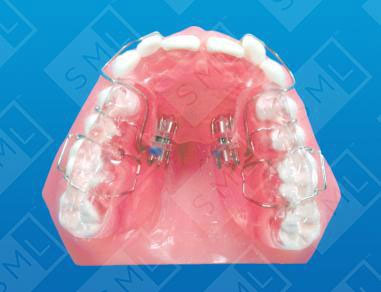
Class II Division 2 Sagittal Appliance U
Patients with a Class II Division 2 skeletal relationship exhibit a combination of a retroclined premaxilla, lingually tipped centrals with overlapping labially placed laterals and a posteriorly placed mandible that is locked into this position by a deep bite.
The first step in correcting this problem is to treat the maxilla by developing the arch in an anterior-posterior direction. The primary objective of the Class II Division 2 Sagittal Appliance is to develop the premaxilla. This is accomplished by the activating the expansion screws and utilizing the extra anchorage created by intercuspating the opposing arch with the posterior bite plane. The laterals can then be guided lingually into place with T-springs. Note: A combination of anterior and posterior occlusal bite planes are commonly used in Sagittal appliances. A wax bite — allowing about 1 to 1-1/2 mm of vertical opening measured between the most posterior teeth in the arch — is needed to properly fabricate the appliance. This bite should be taken in the patient’s natural centric position.

Pre-Maxillary Development Sagittal
The Pre-Maxillary Developement Sagittal appliance is designed to move the pre-maxillary segment labially to regain lost cuspid space and correct an anterior crossbite.
Success is dependent upon excellent retention and proper anchorage. Multiple posterior clasps usually provide enough retention, but a labial arch wire can be added if more is needed. Occlusal coverage aids in appliance retention and can also be indexed heavily to take advantage of inter-arch anchorage. when treating anterior crossbite cases. When treating anterior crossbite cases, opening the vertical dimension with occlusal coverage is essential.
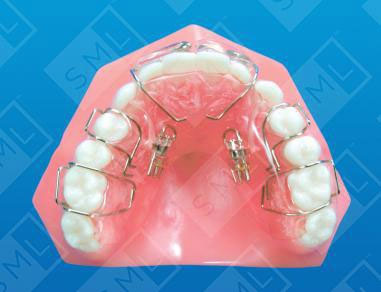
Pre-Maxillary Development Sagittal with Frankel Pads
This Sagittal appliance is designed to move the pre-maxillary segment labially to regain lost cuspid space.
Frankel pads have been added to eliminate lip pressure on the anteriors and facilitate alveolar development of the maxilla. Holding the upper lip forward creates the tension needed to stimulate the periosteum over the maxillary labial plate. Note: Many clinicians prefer to add occlusal coverage to these appliances to aid in retention. Occlusal coverage can also be indexed heavily to take advantage of inter-arch anchorage.

Sagittal with Recurved Springs
Pre-maxillary development alone is not always sufficient to correct a Division 2 malocclusion.
Sometimes the anteriors need to be tipped labially to gain additional arch length. Recurved springs lingual to the centrals provide a controlled labial force, tipping the centrals and increasing arch length. Placing small composite buttons or ledges on the lingual aspect of these teeth is often helpful in maximizing spring effectiveness. Note: Many clinicians like to add occlusal coverage to these appliances to aid in the retention. Occlusal coverage can also be indexed heavily to take advantage of inter-arch anchorage.

Upper Anterior Developer
When upper anteriors are lingually positioned, the upper cuspids are often blocked out of the arch form.
To gain room for the cuspids, the anteriors must first be moved back into their normal position. This design employs the use of a single expansion screw to uniformly torque the four incisors labially. A labial bow is placed from lateral to lateral to aid in appliance retention and to provide an attachment point for the T-springs that will be used to move the cuspids back into the arch form. As with all appliances, sequencing the movements is important. The incisors must be moved to gain space prior to activating the T-springs. Note: The labial bow is carefully bent so that the distal crossover point will not interfere with your ability to reposition the cuspid.

Upper Sagittal to Distalize Molars
Sagittals employed to distalize upper first molars are primarily used to treat Skeletal Class I Dental Class 2 cases and Skeletal Class II Dental Class 2 cases.
Adequate anchorage is the key to successfully moving molars. The anterior teeth, along with the palatal acrylic, labial bow and Adams Clasps comprise this anchorage unit. When it is possible, the anchorage unit should even include the bicuspids. Doing so will make it unnecessary to cover the occlusal surfaces with acrylic. WARNING: Distalizing molars can cause the patient’s bite to open. This is great for skeletal deep bite cases but often very difficult to manage in open bite scenarios. Note: Distal movement of the molars is much easier when the second molars have been removed or when they have not yet erupted. When second molars are not yet erupted, it is important to check their position to be certain that first molar distalization will not create an impaction. This can easily be accomplished by taking an x-ray of the second molars. In some cases, removal of the second molars may be indicated.
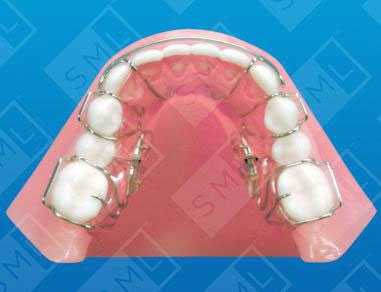
Lower Molar Distalizing Sagittal
Early loss of primary teeth can allow first molars to drift mesially and block the eruption of the bicuspids.
The removable Lower Molar Distalizing Sagittal uses two expansion screws with the acrylic cuts placed just mesial to the molars. By adjusting the expansion screws (1/4 turn once each week), the part of the appliance mesial to the screws acts as an anchor, while the molars are moved distally. When second molars are not yet erupted, it is important to check their position and be certain that first-molar distalization will not create an impaction. This can easily be accomplished by taking an x-ray of the second molars. Note: In some cases, removal of the second molars may be indicated.

Upper Sagittal to Distalize Posterior Segments U
When primary molars are lost prematurely, bicuspids will often erupt mesially — eliminating the space in the arch needed for the cuspids.
When this occurs, the bicuspids and the first molars need to be moved distally to regain the cuspid space. This can be accomplished with this Upper Sagittal design. It uses two sagittal screws with the cut in the acrylic just mesial to the first bicuspids. By the nature of the design, some reciprocal movement of the anteriors will occur. To assure that the majority of the movement is in the distal direction, it is imperative that the second molars are removed and smooth occlusal bite planes placed over the posteriors — this to eliminate any occlusal forces that might interfere with the distal movement. Appliance anchorage is of primary concern and is achieved by using multiple clasping (illustrated by use of four Adams Clasps). This appliance is best used when the molars and bicuspids are fairly well aligned along the posterior arch. Note: Many practitioners like to add cuspid retraction hooks to this appliance. This allows them to retract the cuspids at the same time that the space is created.

Lower Sagittal to Distalize Posterior Segments L
When there is not sufficient space for all teeth to erupt into their ideal position, it is important to determine the cause for this deficiency.
As shown, arch length is less than ideal because due to early loss of primary molars and cuspids. The first molars and bicuspids erupted mesially. To regain space for the cuspids, the posterior segments need to be moved back to their normal position. This sagittal design uses two screws with the cut in the acrylic ( just mesial to the first bicuspids) to regain the lost space. As the space is regained, cuspid retraction springs are used to guide the cuspids into position. Note: second molars are not present. Once they have erupted, distalization of the posterior segments becomes very difficult with this design. Therefore, when your evaluation indicates that the arch length needs to be gained in a distal direction, second molar removal should be part of your treatment plan. By the nature of the appliance design, some reciprocal movement of the anteriors will always still occur.
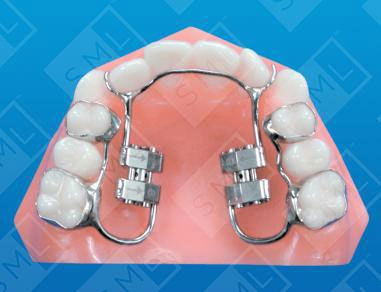
A/P Fixed Sagittal U
A Fixed Sagittal can be used when arch length increase is required in a non-compliant patient or when a patient experiences speech difficulties when wearing an acrylic removable Sagittal.
With the second molars removed (shown), the arch length gain is achieved predominantly by distalization of the posterior segments. With the second molars in place, movement of both the anteriors and posteriors will occur. If movement of the anteriors alone is desired, the cuspids will need to be combined with the bicuspids and molars to create a posterior anchorage unit.

M Pendulum
The M-Pendulum produces AP changes via distalization and rotation of the maxillary first molars.
To accomplish this, .032 TMA springs are engaged into .036 lingual tubes that are soldered to the molar bands — delivering a light continuous force to the molars. The anterior anchorage needed to accomplish this movement is gained through the use of occlusal bonded rests on the pre-molars. if added retention is desired, bands can be used on the bicuspids in place of the rests. Note: this appliance incorporates the innovative M-Pendulum spring design — an inverted horizontal loop placed half way between the spring helix and the .036 molar tubes. The design overcomes the standard Pendulum spring’s tendency to cause cross bites and leave the molar roots mesially inclined. By simply opening the horizontal loop, a buccal and/or distal uprighting force is created — producing a bodily movement of the molars.
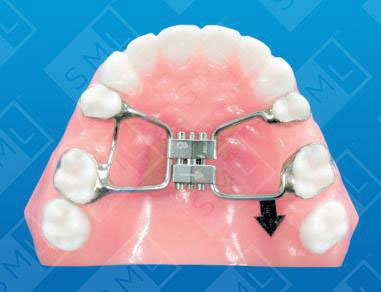
Fixed Unilateral Distalizer
This appliance utilizes a unique expansion screw and fixed anchorage system to allow movement of a single molar, distally, on only one side of the arch.
When space has been lost unilaterally, you can easily distalize the offending molar up to 8mm. Easy to keep clean, it’s also ideal for the non-compliant patient.

CD Distalizer U/L
This popular molar distalizer can be used on either arch and can also be used in a unilateral or bilateral configuration.
The anterior portion typically attaches to the first bicuspid bands with a Nance Button — and often with an additional lingual wire for anchorage. Vertical tubes on the buccal aspect of these bicuspid bands accept the .032 guide wires that run back through the horizontal tubes on the molar bands. Gurin Locks and open coil springs are placed to provide the necessary distalizing force to the molars.
Adjustments are made approximately every 3-4 weeks. Vertical tubes allow it to be placed segmentally, by first cementing the anterior segment, and then placing the molar bands (with .032 guide wires inserted in the tubes) as individual units. The appliance shown here is a depiction of the force module needed to distalize #14 — and also of the use of the Gurin Lock to maintain the already distalized #3. Note: When selecting this appliance, please provide the lab with detailed instructions.

Modified CD Distalizer U/L
This appliance works in much the same way as the CD Distalizer.
However, the design has been modified with the guide wires soldered to the first bicuspids (rather than using the vertical tube assembly to attach them to the bicuspids). Advantages: superior strength and added patient comfort — attachments to the bicuspids are smooth and reduced in overall bulk. Although this design requires all four bands to be seated at once, this is typically not a problem. Appliance shown depicts the force module necessary to distalize #14 — and use of the Gurin lock to maintain the already distalized #3. Note: Gurin Locks and open coil spring provide the necessary distalizing force to the molars.

3-Way Expander
The unique 3-Way Expander features three independently expanding sections in one housing — for transverse as well as sagittal anterior development.
Each section can be independently activated. When an equal amount of lateral development is desired, turn the two lateral sections at the same time. If a differential amount of lateral development is needed, by turning one of the lateral sections, the rest of the appliance will act as an anchorage unit — making unilateral movement possible. This is an excellent appliance when the size of the palate is large enough to handle the dimension of the screw. Due to its considerable bulk, however, it is not suited for narrow palates or younger patients.

Magill Sagittal to Advance
When both anterior and lateral development are needed, but patient compliance is a problem, the fixed Magill Sagittal to Advance is an excellent solution.
Shown here, second molars are present. An anchorage unit is created by joining the bicuspids and molars together with metal tubing on the lingual aspect. The tubing accepts a sliding wire which allows the anteriors to move forward when the appliance is activated. Activation is accomplished by engaging the unique buccal drive tubes with an Allen Wrench. Lateral development can be achieved by turning the central screw one turn each week.
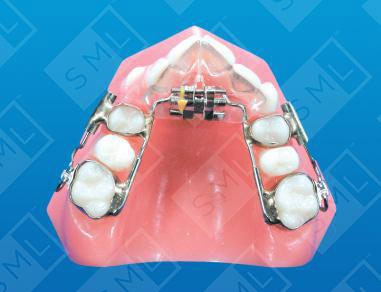
Magill Sagittal to Distalize
When posterior and lateral development are needed, but patient compliance is a problem, the fixed Magill Sagittal to Distalize is an excellent solution.
Essentially the reverse of the Magill Sagittal to Advance this appliance’s drive tubes are anchored to the bicuspids instead of the anterior lingual acrylic. It allows the anteriors to be used for anchorage — by first activating the central screw and then expanding the acrylic segment laterally. Subsequent activation of the buccal drive tubes distalizes the posterior segments. Note: In this example the second molars have been extracted. As with all Distalizing Sagittals, vertical dimension must always be evaluated and second molar removal considered in the interest of expediting treatment.

Nitanium Palatal Expander
The Nitanium Palatal Expander2 (NPE2) is a fixed/removable nickel titanium appliance attached to molar bands via horizontal lingual sheaths.
The main body wire — fabricated from heat activated, nickel titanium wire with shape memory — is formed to a set shape that it maintains when heated above its thermal transition temperature of 94 degrees Fahrenheit. The appliance comes pre-fabricated in several sizes. The appropriate size for a patient is determined by comparing measurement of the patient’s existing arch width to the ideal arch width chosen as your treatment goal.
Clinically, before appliance delivery, the NPE2 is chilled and becomes extremely flexible and easy to insert. As the mouth begins to warm the appliance, the body wire becomes stiffer as shape memory is restored. This exerts a continuous low force on the teeth and mid-palatal suture to produce expansion. Appliance adjustment of the body wire is not necessary, but the extension arms can be adjusted to provide a differential amount of expansion in the bicuspid region (if needed). Note: Initially, a patient may experience slight pressure, which can be relieved by sipping a cold fluid or sucking on an ice cube. This feature makes the appliance very “patient friendly” because it allows mitigation of the pressure response.
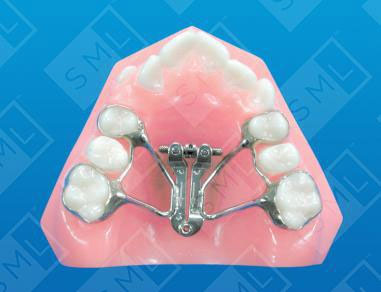
Fixed “Fan-Screw” R.P.E U
Many patients exhibit a V-shaped or Gothic arch form as a result of an abnormal habit or airway problem during development.
When this occurs, the arch may only be narrow in the anterior region. Therefore, use of an expansion appliance that expands equally in the posterior and anterior region would be contra-indicated. The Fixed Fan Screw appliance can produce up to 9mm of lateral arch development, confining the majority of movement to the anterior/cuspid region.
It is typically soldered to bands placed on the first permanent molars and the first bicuspids. Some practitioners prefer to band just the molars. When this is done, it is recommended that the anterior portion of the appliance be secured by placing bonding material over a wire rest.

Wilson 3D Palatal Appliance
The Wilson 3D Palatal Appliance is designed for quick adaptation and easy plug-in and removal from the 3D Lingual Tubes.
It is extremely responsive to palatal bridge activator adjustment utilizing the diamond adjustment wire.
Molar Functions:
- Rotation
- Contraction
- Bilateral and Unilateral Expansion
- Buccal Crown Tip
- Tipback Resistor
- Lingual Crown Tip
- Lingual Root Tip
- Trans-Palatal Arch
To register for a course, visit: PowerproxDocs.com

Lower Skeletal Expander
This fixed mandibular expander requires minimal patient compliance and provides the Doctor with total control during active treatment.
The midline expansion screw is encased in acrylic for comfort purposes.
The entire appliance can be removed from the fixed molar bands when necessary due to the vertical lingual sheaths placed on the bands. This allows for continuing treatment after arch development without the need to re-band the molars.

Removable Acrylic-Free Expander
When banding is not a desirable option this arch development appliance provides for excellent expansion.
Placing small composite buttons on the buccal of the clasped teeth adds additional retention if needed.
This design is often preferred when hygiene might be a problem. The appliance is easily removable for hygiene while providing the needed stability for arch development.
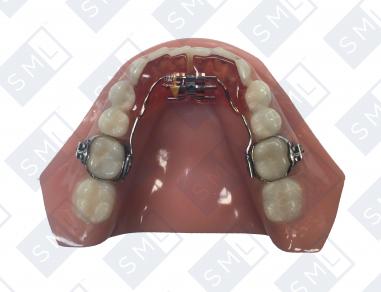
Mandibular Gordon
This Mandibular Gordon is a fixed-removable appliance that is attached to bands via horizontal removable brackets placed on the first permanent molars.
The anterior acrylic portion of the appliance extends back to include the first bicuspids and contains a midline expansion screw.
The Gordon appliance primarily develops the intercanine width but also provides molar expansion and uprighting.

Three-Way Fixed Sagittal (aka Barrel Fixed 3 Way)
A very effective combination distal-driving, transverse development appliance.
This design is typically used to regain lost cuspid space. A common cause for this type of crowding is the early loss of the primary molars. Primary molars normally serve to maintain valuable “E” space for the eruption of the bicuspids and cuspids.
When they are lost early, the permanent first molars drift forward into the areas intended for bicuspid eruption. Consequently, the bicuspid erupts forward into the space intended for cuspid eruption. This Three-Way Sagittal design will regain both arch length and width. Arch width is obtained by transverse expansion.
Arch length is regained by distalizing the posterior segments. Since this is a fixed appliance it provides molar bodily movement and excellent expansion in the posterior region. When distalizing the molars it is recommended to distalize one side at a time before developing transversely. Once the molars are in the desired position and arch width is acceptable the appliance can be removed, a lingual Nance appliance placed to stabilize molar position, the full arch bracket employed to complete bicuspid distalization and anterior alignments.

Lower Bi-Helix
The Bi-Helix Expander shown here on the lower arch is effective for gaining development of the arch while simultaneously achieving an upright position of the molars.
This is accomplished through the position and use of the helix coils lingual to the molars.
The absence of the anterior helixes also provides patient comfort. Note: This design is also effective for the upper arch as well.
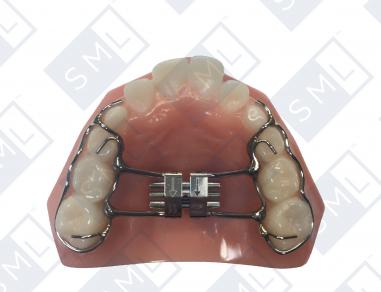
Wire Frame Hyrax
The WireFrame Hyrax is an option when a standard occlusal bonded Hyrax is not desired and then clinical crowns are not sufficiently erupted to allow for banding.
This design can be adequately retained by placing bonding composite over the wire on the buccal of the posterior teeth.
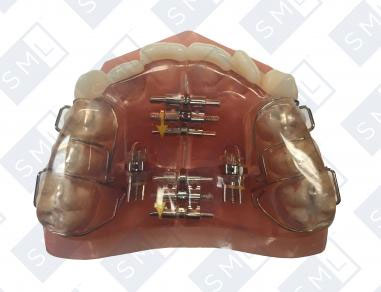
Four Screw Sagittal
Occasionally a second midline screw is added to the standard three-screw Sagittal when lateral as well as AP development is required.
This allows for a limited amount of differential lateral development during treatment as may be deemed necessary for ideal arch form.

Comfort Expander – U/L
The Comfort Expander appliance is designed for maximum comfort and arch development.
This small, low profile expander is uni-body constructed, which provides stability and increases patient comfort and hygiene. It is activated the same way as a standard RPE.
Each appliance includes a complimentary custom swivel key activation tool. Appliance may also be used for combination therapy by adding buccal attachments.
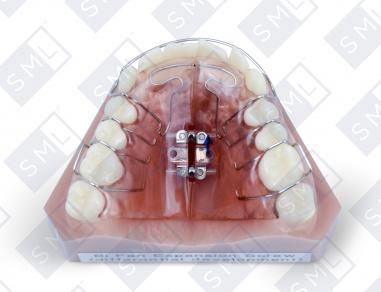
Bi Fan Expansion Screw
Bi Fan Expansion Screw (differential development)
The Bi Fan screw has two turnbuckles that allow for the deferential anterior and posterior expansion of the maxilla.

Fixed Distalizing Sagittal
This Fixed Distalizing Sagittal is commonly used when bodily movement is necessary and patient compliance may be a concern.
It utilizes a lingual acrylic Nance Button for additional anchorage and comfort.
Once the molars are sufficiently distalized the appliance is typically replaced by a fixed lingual arch to maintain molar position during subsequent full arch fixed mechanics.
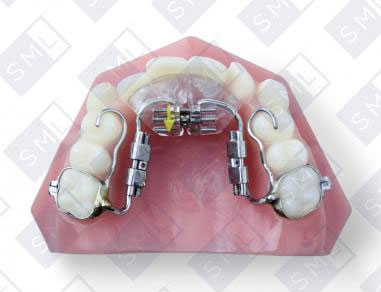
Fixed 3-Way Sagittal
This appliance is used for pre-maxillary and lateral development when patient compliance may be a concern.
The midline expansion screw is placed in acrylic that it finished up against the anteriors. The two laterally placed expansion screws provide the desired pre-maxillary development, while the midline screw can provide any needed lateral development, up to 3mm to 4mm.
The appliance as shown utilizes bands only on the molars. If desired, the occlusal rests on the first bicuspids can be replaced with bands, allow bonding the rests to the occlusal of the bicuspids often is sufficient.

High-Palate (R.P.E.) Hyrax Appliance
In High-Palate (RPE) Hyrax Appliance, the expansion screw is positioned high in the palate for greater comfort.
Bands are placed on the first molars. Rests are bonded to the occlusal surface of the primary molars, thus eliminating the path of insertion problem that occurs when four bands are used.
Extra heavy support wires are also employed to prevent the appliance from flexing as pressure is applied. If you find that a posterior crossbite is locked due to a deep bite or tight intercuspation, it is recommended that a lower occlusal splint be placed temporarily to expedite treatment without affecting the mandibular dentition.